

Patient Basics: Developmental Dysplasia of the Hip (Hip Dysplasia)
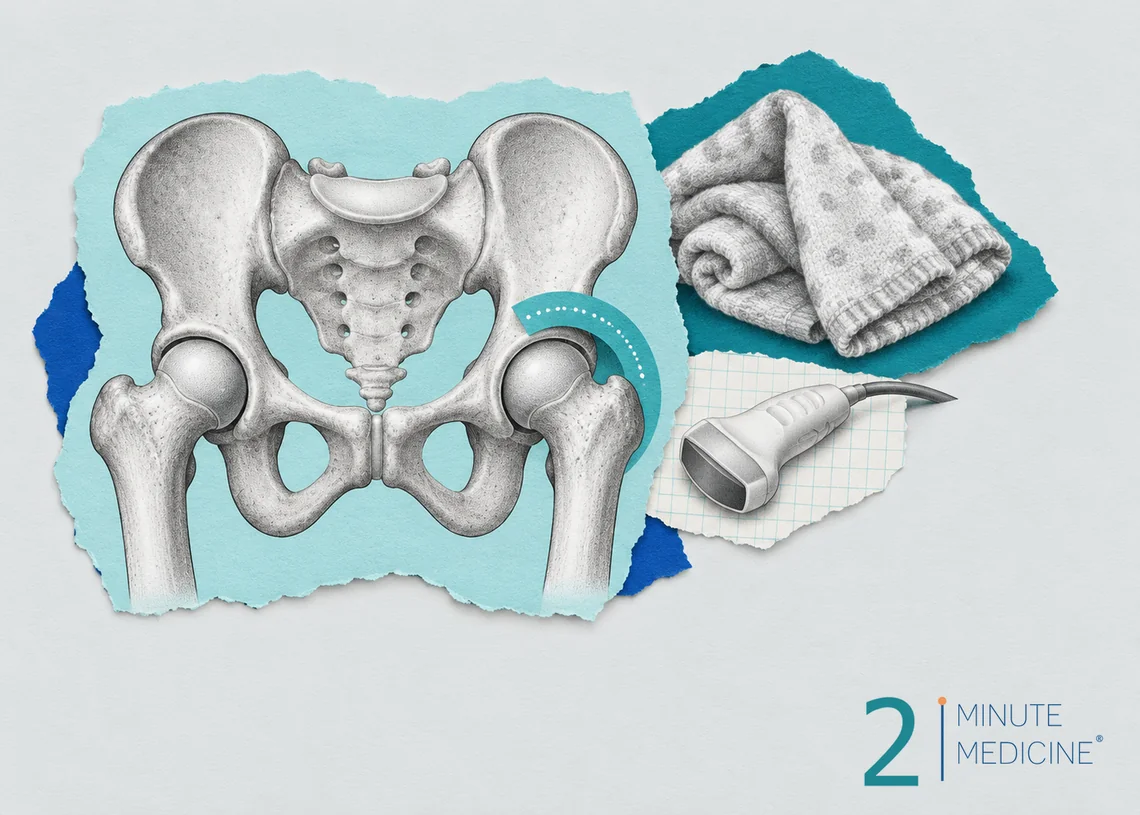
Developmental dysplasia of the hip (DDH), often called hip dysplasia, means a baby’s hip joint hasn’t formed the way it should. The socket is too shallow, so the rounded end of the thigh bone sits loosely and may slip partly or fully out. When it is found early, a soft brace usually fixes it, and most children grow up with normal hips.
Key points
- Doctors check every baby’s hips at birth and at well-baby visits until the child walks.
- Being in a breech position before birth, being a girl, being the firstborn and having a family history raise the risk.
- Ultrasound is the main test in the first few months. X-rays are used after that.
- Most babies found early are treated with a soft fabric brace (a Pavlik harness) for a few months.
- Swaddle babies so their legs can bend up and fall open at the hips.
How a baby’s hip forms
The hip is a ball-and-socket joint. The rounded upper end of the femur (thigh bone) nests in a hollow on the side of the pelvis. At birth, both parts are mostly soft cartilage. They mold each other as the baby grows, but only if the ball sits snugly in the socket. If the ball is loose, the socket stays shallow.
Hip dysplasia ranges from a slightly shallow socket with a stable hip, to a hip that can be pushed out, to one that is fully out of place. It used to be called congenital dislocation of the hip. The name changed because the problem can show up or get worse after birth.
What causes hip dysplasia in babies
Several things make it more likely:
- Breech position in the last weeks of pregnancy, especially frank breech, where the baby is bottom-down with the legs pointing straight up
- Being a girl. Girls are affected several times more often than boys.
- Being the first baby, when there is less room in the womb
- A parent, brother or sister who had hip dysplasia
- Low fluid around the baby during pregnancy
- Tight swaddling with the legs held straight and together after birth
The left hip is affected more often than the right, and sometimes both hips are. Many babies with DDH have none of these risk factors, and nothing the parents did caused it.
Signs of hip dysplasia in babies
Babies with hip dysplasia usually aren’t in pain, and many show no signs at all. Things a parent or doctor might notice:
- One leg doesn’t open out to the side as far as the other during diaper changes
- One leg looks shorter, or one knee sits lower when the baby lies on their back with knees bent
- Uneven skin creases on the thighs or buttocks. Many healthy babies have uneven folds, so this matters most along with other signs.
Once a child walks, signs can include a limp, walking on the toes of one foot, leaning to one side, or a waddling walk if both hips are affected.
How doctors check for it
- Exam. The doctor gently bends the baby’s legs and moves each hip to feel whether the ball slides out of or back into the socket. These checks are repeated at well-baby visits. Small clicks are common and usually harmless. A clunk as the hip moves in or out is the sign doctors look for.
- Ultrasound. Before about 4 to 6 months, the hip is mostly cartilage, which shows up well on ultrasound. Babies with risk factors, such as breech girls, are often checked at about 6 weeks even if the exam is normal.
- X-ray. After about 4 to 6 months, bone has started to form and X-rays work better. On a normal hip X-ray, a deep socket covers the ball. With dysplasia, the socket is shallow and sloping, and the ball sits higher or partly outside it.
How hip dysplasia is treated
Treatment depends on the baby’s age and how loose the hip is. The aim is to seat the ball deep in the socket.
A slightly loose hip in the first few weeks often tightens up on its own, so your doctor may simply repeat the exam or ultrasound a few weeks later.
Pavlik harness, from birth to about 6 months
This soft brace has straps over the shoulders and around the legs. It holds the knees bent up and apart in an M shape, which guides the ball into the socket. Babies usually wear it day and night for 6 to 12 weeks, then for part of the day as it is weaned. Regular ultrasounds check progress. The team will show you how to change diapers around it. Don’t adjust the straps yourself. The brace works for most babies treated in the first months.
Closed reduction and a spica cast, about 6 to 18 months
If the brace doesn’t work, or the baby is older, a surgeon gently moves the ball into the socket while the child is under general anesthesia. Sometimes a tight tendon in the groin is released through a tiny cut. A body cast (a spica cast) then holds the hips in place for about 3 months.
Surgery for older children
Toddlers and older children may need an operation to open the joint and place the ball in the socket. The surgeon may also reshape the thigh bone or the pelvis to give the ball a deeper cup.
Recovery and follow-up
Children treated for DDH need checkups and X-rays until they finish growing, because a shallow socket can come back. After a cast comes off, stiff, weak legs are common for a few weeks, and normal play usually fixes this. Children treated early usually walk, run and play sports like other children.
Hip dysplasia in teens and adults
Mild dysplasia can go unnoticed until the teen or adult years. It often shows up as groin or hip pain during activity, or a catching feeling in the hip. Over time it can wear out the joint early. Physical therapy helps some people. Younger adults whose joint is still healthy may be offered surgery to turn the socket so it covers the ball better. People with arthritis may need a hip replacement.
Lowering your baby’s risk
- Swaddle snugly around the arms and chest but loosely around the hips, so the legs can bend up and out.
- Choose baby carriers and car seats that support the thighs with the knees apart.
- Keep all well-baby visits.
- Tell your baby’s doctor if your baby was breech or a family member had hip dysplasia.
When to see a doctor
- One leg spreads less, looks shorter or turns out more than the other
- Your child limps, walks on tiptoe on one side or waddles
- A teen or adult has ongoing groin or hip pain with activity
- A baby in a brace has red or broken skin, or stops kicking one leg
Common questions about hip dysplasia
Can DDH be cured?
Yes, in most children. When hip dysplasia is found in the first few months and treated with a brace, the hip usually grows normally. Children found later often need a cast or surgery but can still do well. Follow-up until growth ends helps catch any problem that returns.
Does hip dysplasia hurt a baby?
Usually not. Babies with hip dysplasia rarely seem uncomfortable, which is why routine hip checks matter. Most babies get used to a Pavlik harness within a few days. Pain tends to appear only years later, in teens or adults whose dysplasia was never treated.
Can swaddling cause hip dysplasia?
Tight swaddling with the legs held straight and pressed together can raise the risk. Most cases come from the baby’s position in the womb and family traits. Hip-healthy swaddling keeps the wrap loose around the hips so the legs can bend up and fall apart.
Questions to ask your doctor
- How loose is my baby’s hip?
- Does my baby need an ultrasound, and when?
- How long will the brace be needed, and how do I care for my baby in it?
- What happens if the brace doesn’t work?
- How long will my child need checkups?
Learn more
- Developmental dysplasia of the hip (MedlinePlus, U.S. National Library of Medicine)
- Developmental dysplasia of the hip (NHS)
This guide is general information and doesn’t replace advice from your own doctor. Last updated October 2026.
RelatedReports








 Get the app