

Patient Basics: Osteoporosis

Osteoporosis is a disease that makes bones thin and fragile, so they break easily, often from a simple fall or even a cough. It usually causes no symptoms until a bone breaks, which is why a bone density test matters. About half of women and up to 1 in 4 men over 50 will break a bone because of it. Medicines, exercise, and enough calcium and vitamin D can strengthen bones and cut the chance of a fracture.
Key points
- The hip, spine and wrist are the bones most likely to break.
- Women should have a bone density (DXA) test at 65, or earlier after menopause if they have risk factors.
- A T-score of -2.5 or lower means osteoporosis.
- Bisphosphonate pills are the usual first treatment. Shots that build new bone are used for people at very high risk.
- Preventing falls is as important as treating the bones.
How bones become weak
Bone is living tissue. Your body is always breaking down small amounts of old bone and laying down new bone. Bones are at their densest around age 30. After that, loss slowly outpaces building. In women, the drop in estrogen at menopause speeds up bone loss for several years. Over time, the honeycomb-like inside of bone develops bigger holes and thinner walls, and the bone loses strength.
Who gets osteoporosis
Anyone can, but the risk is higher with:
- Being a woman, especially after menopause
- Older age
- A parent who broke a hip
- A small, thin body frame
- Smoking, or more than 2 or 3 alcoholic drinks a day
- Low calcium or vitamin D, or little physical activity
- Long-term use of steroid pills such as prednisone, some seizure medicines, some breast and prostate cancer treatments, or too much thyroid medicine
- Conditions such as rheumatoid arthritis, celiac disease, an overactive thyroid or parathyroid gland, low testosterone, eating disorders, diabetes and kidney disease
Osteoporosis symptoms
Thinning bones don’t hurt. Signs appear once bones start to break:
- A broken bone from a fall from standing height or less
- Sudden back pain, from a collapsed bone in the spine (compression fracture)
- Losing more than an inch and a half of height
- A rounded upper back or stooped posture
Some spine fractures cause little pain and are found only on an X-ray.
Bone density test and T-score
A DXA scan (dual-energy X-ray absorptiometry) measures bone density in the hip and lower spine. You lie on a padded table for about 10 to 20 minutes while an arm passes over you. It’s painless and uses very little radiation.
The result is a T-score, which compares your bones with those of a healthy young adult:
- -1.0 or higher: normal
- Between -1.0 and -2.5: low bone mass (osteopenia)
- -2.5 or lower: osteoporosis
A hip or spine fracture from a minor fall also counts as osteoporosis, whatever the T-score. Your doctor may use a tool called FRAX to estimate your chance of a major fracture over the next 10 years. Blood tests check calcium, vitamin D, kidney and thyroid function, and other causes of bone loss. Some doctors also measure bone turnover markers in the blood to see how well treatment is working.
Women should be screened at 65, and younger women after menopause should be screened if they have risk factors. Many experts suggest testing men at 70, or earlier with risk factors.
Osteoporosis treatment
Bone health habits
- Calcium. Get it mostly from food, such as dairy, fortified plant milks, canned fish with soft bones, tofu and leafy greens. Take a supplement only if your diet falls short.
- Vitamin D helps your body absorb calcium. Many adults need a supplement.
- Exercise. Walking, stair climbing and strength training with weights or bands build and keep bone. Balance exercise such as tai chi lowers the chance of falling.
- No smoking, and limit alcohol.
Medicines
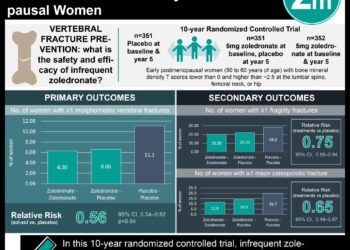
- Bisphosphonates slow bone loss. Pills include alendronate and risedronate, taken weekly or monthly, and ibandronate, taken monthly. Take them first thing in the morning with a full glass of plain water, and stay upright and don’t eat for at least 30 minutes. Zoledronic acid is given by IV once a year.
- Denosumab (Prolia) is a shot every 6 months. Don’t stop it or delay a dose without a plan from your doctor, because bone loss and spine fractures can come back quickly.
- Bone-building drugs are for people at very high risk. Teriparatide (Forteo) and abaloparatide are daily shots, usually for up to 2 years. Romosozumab (Evenity) is a monthly shot for one year, and it isn’t used after a recent heart attack or stroke. Afterward, you switch to a bisphosphonate or denosumab to keep the new bone.
- Raloxifene is a pill for women that protects the spine and lowers breast cancer risk, but it raises the chance of blood clots.
- Estrogen hormone therapy around menopause can protect bone in some women.
Heartburn is the most common side effect of bisphosphonate pills. Two rare problems, jawbone damage and an unusual thigh fracture, are linked to long-term use of bisphosphonates and denosumab. Tell your dentist about these medicines, and report new thigh or groin pain. After 3 to 5 years, some people can take a break from bisphosphonates.
Preventing falls
- Remove loose rugs and clutter, and add grab bars and night lights.
- Wear sturdy shoes with non-slip soles.
- Have your vision checked every year.
- Ask whether any of your medicines cause dizziness or drowsiness.
When to see a doctor
- You’re a woman 65 or older and haven’t had a bone density test
- You broke a bone in a minor fall after age 50
- You’ve lost height or your back is becoming rounded
- You take steroid pills or another medicine that thins bone
Get emergency care after a fall if you can’t stand or put weight on a leg, or if you have severe back pain.
Common questions about osteoporosis
Can osteoporosis be reversed?
Not completely, but it can improve. Treatment can raise bone density, especially bone-building shots, and medicines can lower the chance of a spine fracture by about half or more. There’s no cure, so most people need some form of treatment or monitoring for life.
Is osteoporosis hereditary?
Partly. Your genes help set how much bone you build by early adulthood. If a parent broke a hip, your own risk is higher. You can’t change your genes, but exercise, calcium, vitamin D, not smoking and early testing can make a big difference.
What is the best and safest treatment for osteoporosis?
For most people, bisphosphonates are the first choice. They have decades of use and serious side effects are rare. People at very high risk often do better starting with a bone-building drug. The best choice depends on your fracture risk, kidney function, other health conditions and preferences.
How long does Forteo stay in your system?
Teriparatide (Forteo) clears from the blood within a few hours of each shot. Its bone-building effect lasts longer, but the gains fade over months after you stop. That’s why doctors follow it with a bisphosphonate or denosumab to lock in the new bone.
Questions to ask your doctor
- What is my T-score, and what is my risk of a fracture?
- Do I need a medicine, and which one fits me best?
- How long should I take it?
- Should I take calcium or vitamin D supplements?
- When should I repeat my bone density test?
Learn more
- Osteoporosis (National Institute of Arthritis and Musculoskeletal and Skin Diseases)
- Osteoporosis (MedlinePlus, U.S. National Library of Medicine)
This guide is general information and doesn’t replace advice from your own doctor. Last updated October 2026.
RelatedReports







 Get the app