

Patient Basics: Psoriasis
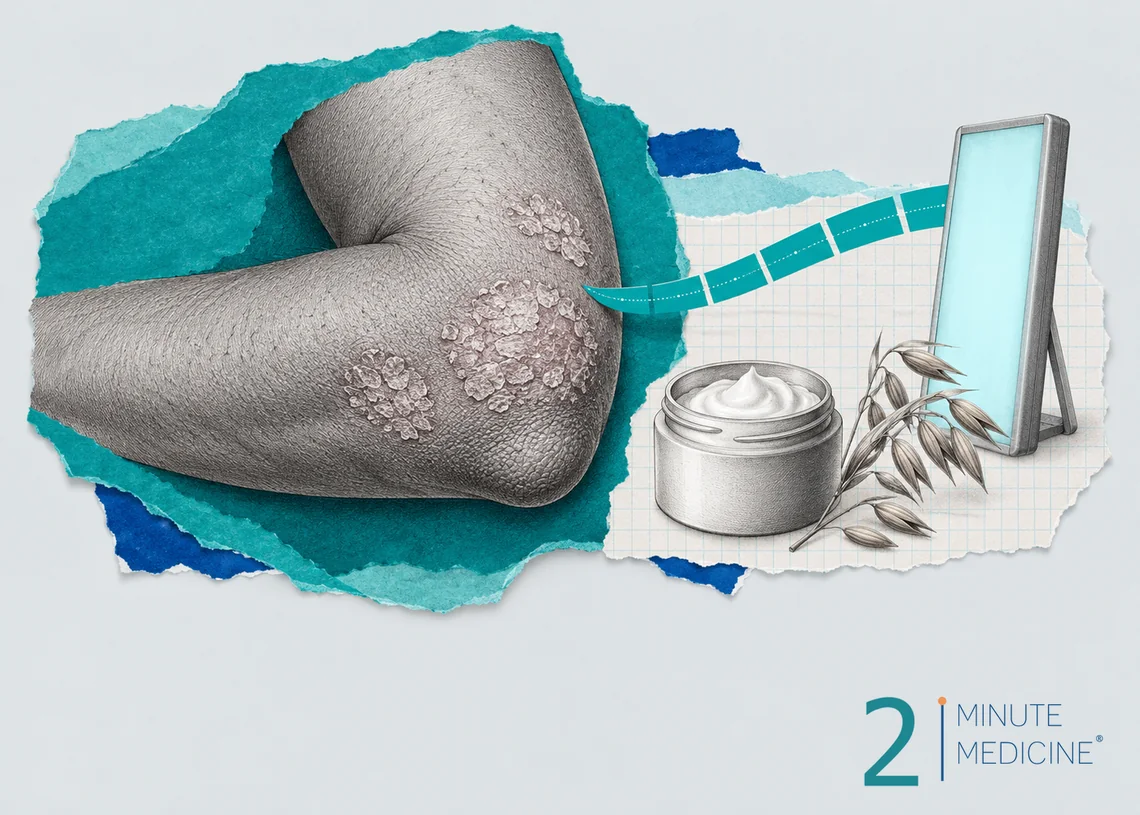
Psoriasis is a lifelong skin disease in which an overactive immune system makes skin cells grow far too fast. The extra cells pile up into thick, scaly patches, most often on the elbows, knees, scalp and lower back. Psoriasis isn’t contagious, and while there’s no cure, today’s treatments can clear the skin or nearly clear it for most people.
Key points
- About 3 in 100 adults in the US have psoriasis. It often starts between ages 15 and 35 but can begin at any age.
- It tends to come and go, with flares set off by things like strep throat, stress, skin injury and some medicines.
- Up to 1 in 3 people with psoriasis develop psoriatic arthritis, which causes joint pain and swelling.
- Treatments include creams, light therapy, pills and injected biologic medicines.
- Psoriasis raises the risk of heart disease, diabetes and depression, so overall health checks matter.
What causes psoriasis
Normally, skin cells take about a month to form, rise to the surface and shed. In psoriasis, immune cells send out signals (such as IL-17 and IL-23) that speed this up to a few days. The skin can’t shed the cells fast enough, so they build up into raised plaques. Genes play a big part, and psoriasis often runs in families.
Common triggers for a flare include:
- Infections, especially strep throat
- Cuts, scrapes, sunburn, tattoos or scratching. New patches can form where the skin was hurt.
- Stress
- Cold, dry weather
- Smoking, heavy drinking and extra weight
- Some medicines, such as lithium, some blood pressure drugs called beta-blockers, and hydroxychloroquine, or stopping steroid pills suddenly
Types of psoriasis
- Plaque psoriasis is by far the most common. Patches are raised and well-defined, with a silvery-white scale. On light skin they look pink or red. On brown and Black skin they may look purple, dark brown or gray, which can make them harder to recognize.
- Scalp psoriasis causes thick scale and flaking that can spread past the hairline and behind the ears.
- Nail psoriasis causes tiny pits, yellow-brown spots, thickening, or nails lifting from the nail bed.
- Guttate psoriasis appears suddenly as many small, drop-shaped spots, often in children and young adults after strep throat.
- Inverse psoriasis forms smooth, shiny patches without much scale in skin folds, such as the armpits, groin and under the breasts.
- Pustular psoriasis causes pus-filled bumps that aren’t infected, usually on the palms and soles. Rarely, it spreads over the body.
- Erythrodermic psoriasis is rare and serious. Most of the skin turns red and peels.
Patches may itch, burn or crack and bleed, especially on the hands and feet.
Psoriatic arthritis
Psoriatic arthritis can start years after the skin problem, or occasionally before it. Watch for stiff, painful joints in the morning, a whole finger or toe that swells like a sausage, heel pain, or low back pain. Tell your doctor early, because treatment can prevent lasting joint damage, and some psoriasis medicines treat both.
How psoriasis is diagnosed
A doctor or dermatologist can usually tell by looking at your skin, scalp and nails and asking about your family history. There’s no blood test for psoriasis. If the rash looks unusual, a small skin sample (biopsy) can rule out eczema, fungal infection and other conditions.
How psoriasis is treated
Treatment depends on how much skin is involved, where the patches are, and how much they affect your life. Patches on the face, hands, feet, scalp or genitals can be treated more strongly even if they’re small.
Treatments you put on the skin
- Steroid creams and ointments calm inflammation. Stronger ones are used on thick patches and milder ones on the face and skin folds.
- Vitamin D-like creams such as calcipotriene slow skin growth. They’re often combined with a steroid.
- Newer non-steroid creams, roflumilast and tapinarof, can be used long term, including on sensitive areas.
- Salicylic acid and coal tar soften scale. Medicated shampoos help scalp psoriasis.
Light therapy
Narrowband ultraviolet B (UVB) light, given in a clinic or with a home unit 2 or 3 times a week, slows skin cell growth. It works well for widespread psoriasis. Tanning beds aren’t a substitute, because they raise the risk of skin cancer.
Pills and shots
- Pills such as apremilast, deucravacitinib, methotrexate, acitretin and cyclosporine
- Biologics, injected every few weeks or months, block the immune signals that drive psoriasis. They include adalimumab, etanercept, ustekinumab, secukinumab, ixekizumab, bimekizumab, guselkumab and risankizumab. Many people reach clear or almost clear skin.
These medicines lower parts of the immune system, so you’ll be checked for tuberculosis and other infections before starting, and monitored with blood tests for some drugs. Lower-cost biosimilar versions of several biologics are now available.
Caring for your skin
- Moisturize often with a thick, fragrance-free cream or ointment, especially right after bathing.
- Take short, lukewarm baths or showers. Oatmeal, bath oil or Epsom salts can ease itch and loosen scale.
- Try not to scratch or pick at patches.
- Get small amounts of sun if your doctor agrees, but avoid sunburn.
- Quit smoking, limit alcohol, and aim for a healthy weight. Losing extra weight can make treatment work better.
- Find ways to manage stress, and talk to someone if psoriasis affects your mood or confidence.
When to see a doctor
- A scaly rash that doesn’t clear with moisturizer
- Psoriasis that is spreading or isn’t controlled by your treatment
- Joint pain, stiffness or swelling
- Psoriasis that affects your sleep, work or mood
Get emergency care if most of your skin turns red and starts peeling, or if you have widespread pus bumps with fever, chills or feeling very unwell.
Common questions about psoriasis
Is psoriasis contagious?
No. You can’t catch psoriasis from touching someone’s skin, sharing towels or swimming in the same pool. It comes from the immune system and genes. Guttate psoriasis can follow strep throat, but the strep is what spreads, and the psoriasis itself does not.
Can psoriasis go away?
It can clear for months or years, either with treatment or on its own, but it usually returns at some point. Guttate psoriasis after strep throat sometimes clears and never comes back. Most people have psoriasis for life, with flares and quieter times.
What’s the difference between psoriasis and eczema?
Psoriasis patches tend to be thicker, with sharp edges and silvery scale, often on the outside of elbows and knees. Eczema patches are usually less defined, very itchy, and often in the creases of elbows and knees. Both are immune-related, but they’re treated differently, so a correct diagnosis matters.
Does diet help psoriasis?
No diet cures psoriasis. Losing weight, if you carry extra, can improve it and help medicines work better. Cutting back on alcohol helps too. People with psoriasis who also have celiac disease may improve on a gluten-free diet, but there’s no proof gluten-free eating helps others.
Questions to ask your doctor
- Which type of psoriasis do I have, and how severe is it?
- Which treatment do you suggest first?
- Should I be checked for psoriatic arthritis?
- Would a biologic or light therapy make sense for me?
- Do I need checks for heart disease or diabetes?
Learn more
- Psoriasis (National Institute of Arthritis and Musculoskeletal and Skin Diseases)
- Psoriasis (MedlinePlus, U.S. National Library of Medicine)
This guide is general information and doesn’t replace advice from your own doctor. Last updated October 2026.
RelatedReports





 Get the app